
GDC-compliant website copy and before-and-after photos

Cosmetic pages are where dental websites go to get into trouble. The photographs are the product. The adjectives are the risk. Guidance from the General Dental Council on advertising, and the broader duty not to mislead, does not ban before-and-after images. It does ban the way many clinics still write as if a veneer were a personality upgrade with a guaranteed outcome.
This is a working note for principals and the people who edit their sites. It is not legal advice. It is the pattern of mistakes we see when a ranking or a paid campaign suddenly puts an old page in front of a new audience.
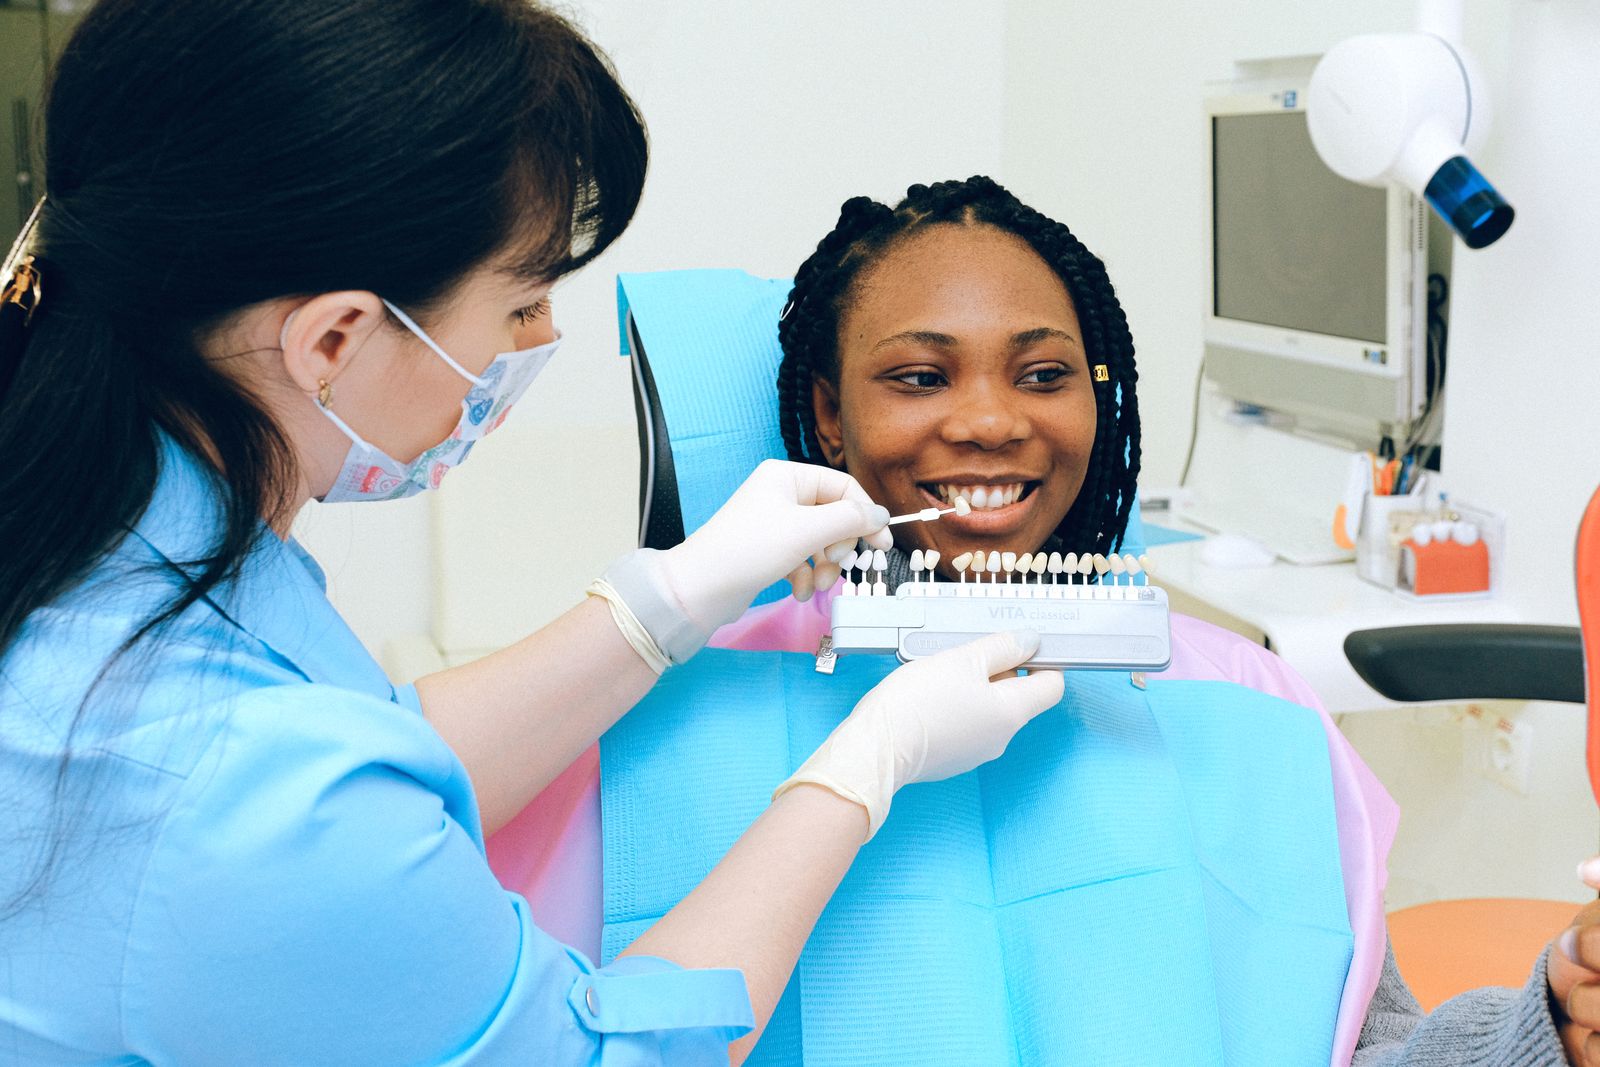
Copy that does not promise a face
Avoid superlatives you cannot defend: “best smile in Manchester”, “pain-free always”, “guaranteed Invisalign in six months”. Avoid implying a celebrity result. Be precise about what the treatment is, who it may not suit, and that an assessment decides suitability. Fees, if you publish them, should be honest about “from” and about what the figure excludes. Scans, sedation, laboratory, review visits.
Testimonials need to be genuine, permissioned and not cherry-picked to invent a clinical claim the dentist would not write themselves. Five-star widgets are not a substitute for that judgement. If a review makes a medicinal claim, it should not be the hero sentence on the implant page.
Before-and-after rules of thumb
Use real patients who have given specific consent for website and ads, not a blanket “we may use photographs”. Keep lighting, crop and expression comparable so you are not selling a better camera. Label the treatment actually provided. Do not retouch teeth. Do not use stock dentistry grins next to a “our patients” caption. If you would be uncomfortable explaining the image to a complainant, it is not ready.
A short caption beats a moodboard: treatment, timeframe, that individual results vary. If the case needed restorative work as well as aligners, say so. The lie by omission is the one that travels.
Who is on camera
Identifiable patients are not decoration. Minors need a higher bar; in practice, do not use children’s faces for marketing unless you have a specific, documented reason and consent that would survive scrutiny. Staff photographs are simpler but still need consent if you are running them in ads. The “team” page is not a loophole for a Meta campaign.
A publishing workflow
One clinician signs off treatment pages. The TCO does not publish a new gallery on a Friday because the photographer delivered files. Keep a register of consents against URLs. When a patient withdraws, the image has to be removable from the site, the ads manager and the CDN, not just “the next web update”. That last part is where practices discover they never owned the folder.
If you run NHS and private on one domain, keep the promises from crossing. A private bonding gallery that sits above an NHS “register” form will be read as one offer. The GDC cares about what a reasonable person takes away, not what your designer grouped in Figma.
Paid ads inherit the page
A compliant website can still become a non-compliant ad. The Meta crop that drops your caption, the Google RSA that invents “best dentist”, the before image used as a scare thumbnail. Those are your problem when someone complains. Keep a folder of approved headlines. Ban “celebrity smile” language in the ads account, not only on WordPress. If an agency runs the account, put the GDC advertising guidance in the contract and require written approval for new creative that uses clinical photographs.
Landing pages built only for paid traffic need the same consent trail as the main site. “It’s just a funnel” is not a category the GDC recognises. If the photograph is on the internet with your name under it, it is advertising.
Fees, finance and the implied promise
Publishing fees is good manners and good conversion. Publishing them badly is a claim. “Implants from £X” must be a price a real patient can still encounter after assessment, not a loss-leader that only exists if they need nothing else. Finance examples should say representative and name the lender. If you do not offer 0%, do not let an old banner say you do. Mixed practices must not let an NHS patient read a private fee as a band charge, or the reverse.
A quarterly copy audit
Once a quarter, a clinician reads the implant, aligner, bonding and homepage out loud. Anything they would not say in the chair gets cut. Check the gallery consents. Check the team page for people who have left. Check the blog for a guest post that made a whitening claim you no longer stand behind. This takes an hour and prevents the five-year-old paragraph that only surfaces when a journalist or a complainant searches your name.
Keep a changelog. When you alter a claim, date it. If you ever need to show what the site said, a memory of “we were always careful” will not do. The internet remembers the old screenshot even when you do not.
Team pages and titles
Use the titles people are allowed to use. Do not let a copywriter promote someone to a specialist implied by the GDC specialist lists if they are not on them. “Special interest” is not a loophole for a headline. Link GDC numbers. If a clinician leaves, the treatment page that still quotes them as “our implant lead” becomes a complaint waiting for a screenshot. This is copy maintenance, not a rebrand.